
What Are Medical Billing Companies in Vermont?
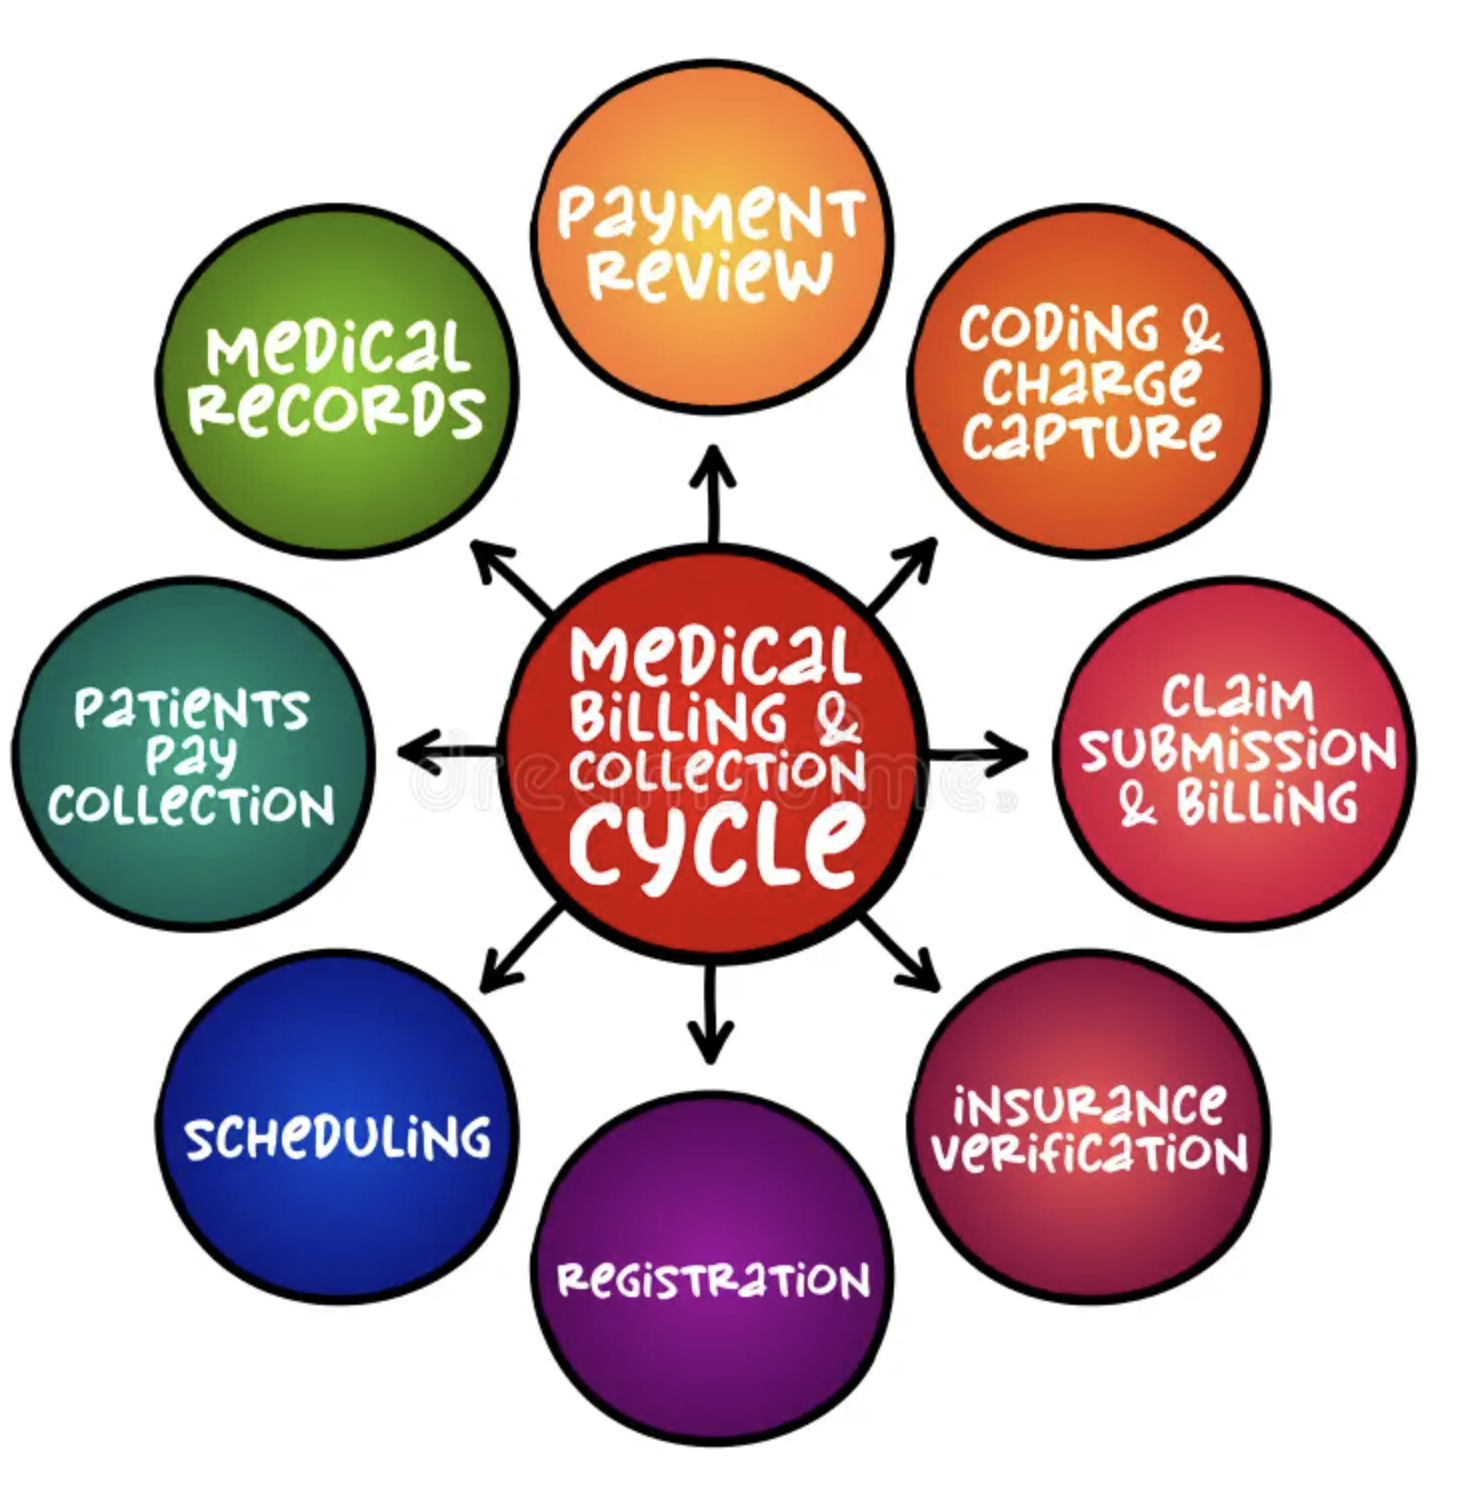
Medical billing companies in Vermont manage claims, payments, denials, appeals, patient balances and related revenue cycle work for healthcare practices. Their work must account for Vermont payer rules, including the requirement under 18 V.S.A. § 9418 that a health plan pay, deny or contest a claim within 30 days of receipt, with interest accruing at 12 percent per year after that.
Vermont Practices Are Losing Revenue in Places They Cannot See
Aged AR and unworked denials are the visible problem. In Vermont the pattern underneath them runs in two directions at once.
The front end is tight. Vermont Medicaid wants the claim within 180 days of the date of service, and holidays, office closures and a pending prior authorization decision do not extend that window by a single day. Miss it and the claim is gone. There is no argument to make.
The back end is the opposite. Vermont gives providers unusually strong statutory footing: 12 percent annual interest on a late payment, a hard 12-month ceiling on recoupment, and a prior authorization request that is deemed granted when the plan misses its own deadline.
Almost nobody here enforces any of it.
So the work is eligibility verification before the visit, certified medical coding on the claim, and somebody still reading the payer’s own deadlines back to it after the money lands.
Medical Billing Services for Vermont Practices
Full-Service Medical Billing
Our full-service medical billing team manages the revenue cycle from eligibility through payment posting and zero balance. Your dedicated team works inside your existing practice management or EHR system instead of forcing you through a disruptive software migration.
Medical Coding
Our certified medical coders review documentation and apply the appropriate coding workflows for your specialty and payer mix. Better coding upstream can prevent avoidable denials downstream.
Denials and AR Recovery
Old accounts are often the fastest place to find recoverable revenue. Our denials and AR recovery service prioritizes aged accounts, identifies denial patterns, works payer responses, and pursues appropriate appeals and follow-up until the account reaches resolution.
Eligibility and Benefits Verification
Eligibility problems can create avoidable write-offs and patient-balance confusion. We verify coverage and benefits so your team has the information needed before claims and patient statements move forward.
Prior Authorization
Authorization requirements vary by payer, plan, service, and specialty. We manage prior authorization workflows so required approvals are addressed before services become preventable billing problems.
Patient Billing
Patient balances are part of the revenue cycle too. Our patient billing support keeps statements, balances, and follow-up organized so your practice is not leaving the final portion of earned revenue unattended.
Credentialing
Credentialing problems can delay payments before the first claim is ever submitted. We support provider enrollment and credentialing so practices stay operational with the plans they serve.
RCM, CCM and Telehealth
Practices increasingly need billing workflows that account for multiple care models and remote services. We support revenue-cycle processes for RCM, chronic care management, and telehealth programs, with medical virtual assistant support where a practice needs front-office coverage alongside billing.
Dashboards and Automations
You should not need to wait for a monthly spreadsheet to understand what is happening to your revenue. We use reporting and workflow automation to make trends in AR, denials, collections, and billing performance easier to identify and act on.
How Our Medical Billing Process Works
1. Start With a Billing Review
We begin with a 30-minute review of your AR aging, denial patterns, payer mix, and current billing workflow. The goal is simple: identify what is actually costing you money and where we would start.
2. Build the Revenue Recovery Plan
We identify the accounts, payer issues, coding patterns, workflow gaps, and filing risks that deserve attention first. You get a clear view of what should be worked immediately and what needs a process change.
3. Start With the Oldest Money
Working aged AR comes first because it represents revenue you have already earned. Our team works the backlog while establishing a consistent process for new claims and daily billing.
4. Run the Full Cycle
Once the foundation is in place, we take over the agreed portion of the revenue cycle: eligibility, coding, submissions, payment posting, denials, appeals, AR follow-up, patient billing, and reporting.
5. Improve the System, Not Just the Claims
The goal is not to create a permanent cycle of denials and appeals. We look for repeatable patterns so the practice can prevent the same billing problems from occurring again.
Why Vermont Practices Choose Luxen
20+ Years of Revenue Cycle Experience
Medical billing is not a process you learn from a checklist. Payer behavior, documentation, coding, authorization, and follow-up all require experience. Luxen brings more than two decades of experience to the revenue cycle.
Certified Coders
Coding quality affects everything downstream. Our billing operation includes certified coding expertise so claims are built with greater attention to documentation and payer requirements.
Your Existing EHR and Practice Management System
You do not have to replace the software your practice already uses. Luxen works within your existing system, including platforms such as athenahealth, DrChrono, ModMed, AdvancedMD, NextGen, eClinicalWorks, Meditab, OpenDental, and other systems.
A Named Team, Not a Random Support Queue
You should know who is responsible for your claims. Our model is built around dedicated people working inside your systems and learning the way your practice operates.
HIPAA-Compliant Workflows
Before accessing protected health information, we sign a business associate agreement, and healthcare engagements operate through HIPAA-compliant tooling.
AAPC, AHIMA and SOC 2
Luxen combines billing expertise with professional credentials and documented security and compliance standards, including AAPC and AHIMA expertise, HIPAA-compliant workflows, and SOC 2.
We Read the Numbers Before We Quote
We do not want to sell you a generic percentage based on a generic practice. We look at your AR aging, volume, specialty, payer mix, and denial profile first.




Medical Billing in Vermont: Understanding the Payer Landscape
Vermont gives a practice the shortest payer list in the country. Commercial volume runs almost entirely through Blue Cross and Blue Shield of Vermont and MVP Health Care, both of which file their rates with the Green Mountain Care Board, the state regulator that reviews and approves premium changes each year. Vermont Medicaid, carried to members under the Green Mountain Care name, is administered directly by the Department of Vermont Health Access under the state’s Global Commitment to Health Section 1115 waiver. DVHA is the managed care entity itself. There are no competing Medicaid MCOs to enroll with, no plan-level network rules to track, and none of the county-by-county model structure that California or Texas practices deal with.
That sounds like less work, and on enrollment it is. On risk it is the opposite. When three payers account for most of your remittance, a single edit change or authorization policy can move your entire denial rate inside one month, and there is no diversified book of business to absorb it.
Concentration is why a Vermont denial trend has to be caught in weeks rather than quarters.
Coverage is close to universal, which changes where the money is. Vermont’s uninsured rate was 4.2% against a national rate of 8.2%, third best in the country, on 2024 American Community Survey data. Roughly 96 cents of every Vermont healthcare dollar arrives from a payer rather than a patient. A practice here recovers revenue by working payers, not by chasing self-pay balances.
Then there is the end of the all-payer model, which practices are still absorbing. OneCare Vermont, the state’s only accountable care organization, wound down operations at the end of 2025, and Vermont’s eight-year all-payer ACO agreement with CMS sunset with it. Practices that spent years inside attributed-population reporting and shared-risk arrangements are back to fee-for-service claim discipline. Revenue now depends on whether an individual claim was coded correctly, filed inside the window and appealed when it came back. Vermont is working toward the federal AHEAD model, and until that lands the claims themselves are the whole story.
The prior authorization rule is where Vermont differs most from the states around it. Under 18 V.S.A. § 9418b a plan has 24 hours to approve, deny or identify missing information on an urgent request, and two business days on a completed non-urgent one, with receipt acknowledged inside 24 hours. If it misses any of those, the request is deemed granted. Tracking authorization timestamps is not administrative overhead in Vermont. It is a payment argument.
Vermont Billing Rules That Can Affect Your Revenue
180 days from date of service when Vermont Medicaid is primary; 365 days when another insurer is primary
Timely filing
30 days to pay, deny or contest, then 12% annual interest (18 V.S.A. 9418)
Prompt-pay requirement
Vermont Medicaid (Green Mountain Care)
State Medicaid program
18 V.S.A. § 9418 sets the commercial claim clock. A health plan has 30 days from receipt to pay a clean claim, or to notify the claimant in writing that the claim is contested or denied, with the specific reasons and the additional information it needs. An electronically submitted claim has to be acknowledged within 24 hours after the beginning of the next business day. Contract terms between a plan and a provider can extend the payment period, which is why your payer contracts matter as much as the statute does.
Late payment carries interest at 12 percent per annum. It runs from the day after the 30 days expire on an uncontested claim, or 30 days after the plan receives the additional information it requested on a contested one. On an aged six-figure balance that adds up, and almost no Vermont practice bills for it.
Paid claims stay exposed for 12 months, and not a day longer in the ordinary case. Under § 9418 a plan may not retroactively deny or recover a payment more than 12 months after it was made, outside a narrow set of exceptions for suspected fraud, duplicate payment, services not delivered, duplicate coverage and pending legal action. Before it recovers anything it owes you at least 30 days written notice, and that notice has to name the patient, the date of service, the amount paid, the proposed adjustment and a reasonably specific explanation.
A recoupment letter missing any of those is a defective notice. Structured AR recovery tests the payment age and the notice contents before money leaves the account.
Prior authorization has teeth here. Under § 9418b, missing the 24-hour urgent deadline, the two-business-day non-urgent deadline, the acknowledgment or the missing-information request means the request is deemed to have been granted. An approval also lasts longer than practices assume: it is valid for the duration of the prescribed treatment or one year, whichever is longer, and for treatment running past a year, renewal cannot be required more than once every five years. Practices reauthorize far more often than Vermont law requires them to.
Vermont Medicaid runs on its own clocks and they are short. Claims where Medicaid is primary must be received within 180 days from the begin date of service. Inpatient claims run 180 days from the discharge date, Medicare crossover claims 180 days from Medicare’s processing date, and claims where another insurer is primary get 365 days from the date of service. A claim that was adjusted or recouped has to be resubmitted within 180 days of that adjustment date. Adjustments in your favor must be requested within one year of the original paid date; DVHA can request a recoupment for up to three years from the date of service. Holidays, weekends and days your office is closed do not extend any of it, and waiting on a prior authorization decision is not an accepted reason for a late claim.
Workers’ compensation has a separate statute with its own deadline. Under 21 V.S.A. § 640a an employer or insurer has 30 days from receipt of a bill to pay it or issue a written denial, and that denial must state the specific reasons, describe the additional information needed and request it within 30 days. Unpaid bills accrue interest at 12 percent annually from the first day after the 30 days run out. On the provider side, bills should be submitted within six months of the date you had actual knowledge the services related to a claim. Rates come from Rule 40, the Vermont Department of Labor medical fee schedule.
Vermont Medical Practices We Serve
We bill for the practices Vermont actually has. The state’s outpatient capacity is rural, small and weighted toward primary care, and the billing problems follow that shape.
Family medicine, internal medicine and pediatrics come first. A one or two provider practice carries the full 180-day Medicaid filing risk with no dedicated biller behind it. Nobody is watching the calendar. Behavioral health and substance use treatment are close behind, where authorization volume is high and the § 9418b deemed-granted rule is worth more than anywhere else on this list. We also bill dental practices, physical therapy and outpatient rehabilitation, chiropractic, optometry and ophthalmology, home health and hospice, and ambulance and emergency medical services.
Orthopedics and occupational medicine carry the Rule 40 workers’ compensation exposure, where § 640a gives the insurer 30 days and requires a denial to name what it needs. Federally qualified health centers, rural health clinics and practices affiliated with critical access hospitals are a category of their own: encounter-rate billing, cost reporting and wraparound payments do not behave like standard fee-for-service claims, and a generalist vendor tends to get them wrong. Any practice billing both commercial carriers and Vermont Medicaid needs provider credentialing current with each of them.
Serving Major Vermont Markets
Burlington
South Burlington
Essex and Colchester
Rutland
Barre
Montpelier
Brattleboro
St. Albans
Bennington
Vermont is the second least populous state in the country, and that scale changes what a billing failure costs. Chittenden County, built around Burlington and South Burlington, holds roughly a quarter of the state’s residents and most of its specialty capacity. Rutland, Barre, Montpelier, Brattleboro, St. Albans and Bennington anchor practices that are often the only option for miles. At that size one biller resigning stalls collections for a quarter, and the 180-day window closes on claims while the position is still open. We have seen it. We work remotely inside your existing system, so distance to billing expertise stops mattering. The state is small enough that we see the same carrier behavior across all of these markets in the same week.
We run the same model in other states, with the payer rules, filing windows and Medicaid structure rebuilt for each one. See New Hampshire medical billing, New York medical billing, Massachusetts medical billing, Maryland medical billing, Illinois medical billing, Ohio medical billing, Virginia medical billing, Texas medical billing, Florida medical billing, California medical billing, Georgia medical billing, Delaware medical billing, Alabama medical billing, Michigan medical billing, Utah medical billing, Tennessee medical billing, Connecticut medical billing, Washington medical billing, Hawaii medical billing, Rhode Island medical billing, Alaska medical billing, Missouri medical billing, Montana medical billing, Wyoming medical billing, South Dakota medical billing, Wisconsin medical billing, South Carolina medical billing, Kentucky medical billing, Oregon medical billing, Nevada medical billing, Idaho medical billing, Nebraska medical billing, North Dakota medical billing, New Mexico medical billing, Mississippi medical billing, West Virginia medical billing, and Kansas medical billing, or start from the full list of medical billing companies and what each one charges.
What Vermont Practices Say About Working With Luxen
“Prior authorizations were consuming hours every week and driving denials we could not explain. Luxen introduced a timestamped workflow around Vermont payer deadlines, reduced our authorization-related denial rate from 14% to 5%, and lowered AR over 90 days by $41,000 in one quarter.”
Executive Director,
Outpatient Behavioral Health Practice, Burlington Area, Vermont
“We had Vermont Medicaid claims approaching the 180-day filing deadline and no reliable way to prioritize them. Luxen identified the highest-risk accounts, recovered $24,600 within ten weeks, and gave us a process for catching claims before they become write-offs.”
Practice Manager,
Three-Provider Family Medicine Practice, Central Vermont
The same approach, documented end to end: our ambulance billing case study and dental practice case study.
What Does Medical Billing Cost in Vermont?
3% to 6% of collections
Luxen's pricing generally falls between 3% and 6% of collections, depending on claim volume, specialty, payer mix, and how much of the revenue cycle your practice hands over.
Larger-volume practices can generally access the lower end of the range because billing economics improve as claim volume increases. A smaller or more complex practice may fall toward the higher end because the amount of work per account is greater.
Most Vermont practices sit at the smaller end of that scale.
For comparison, published billing-industry pricing guides commonly place percentage-based medical billing somewhere around the mid-single digits, with higher ranges for smaller or more complex practices.
The more important question, however, is not whether a billing company charges 3%, 4%, 5%, or 6%.
It is what happens to collections after you hire them.
A lower fee attached to weak billing is still expensive.
The Risks of Outsourcing Your Medical Billing
Outsourcing is not automatically the right choice for every practice.
A billing company is a poor fit if you are unwilling to share operational visibility, if the vendor uses a rotating pool of people who do not learn your practice, or if the company cannot explain why your claims are being denied.
There is also a real risk in choosing a vendor that promises aggressive collection improvements without understanding your payer mix and specialty.
That is why Luxen starts with the numbers.
You should see the AR aging. You should understand your major denial categories. You should know what is being worked. And you should know what your billing company believes is realistically recoverable.
The right outsourcing relationship should make your revenue cycle more visible, not less.
How Much Revenue Are You Missing?
Look at your AR aging.
- How much is sitting past 90 days?
- How much is past 120 days?
- Which payers represent the largest outstanding balances?
- What are your top five denial reasons?
- How many claims are repeatedly resubmitted without a clear resolution?
- How much patient responsibility remains uncollected?
- How many claims are approaching a filing deadline?
Those numbers tell a story.
Send us your AR aging and we will tell you where we would start.
A Message From the Luxen Founder
I started Luxen because medical practices should not have to choose between doing great clinical work and running a financially healthy business.
Billing is too important to be treated as an afterthought. When claims are submitted incorrectly, denials sit untouched, or aged AR is ignored, the practice feels it everywhere, from cash flow and payroll to staffing decisions and growth.
Our job is to bring discipline to that part of the business.
We work inside the systems practices already use, build accountable billing workflows, and focus on the revenue that is actually recoverable.
We believe your billing partner should know your numbers, your specialty, your payers, and your practice, not just your account number.
Shivam Pujara
Founder, Luxen Talent (& Madhupa)
More on how we built the Luxen billing team.

Transparent, U.S.-Focused Billing Support
Your Practice Keeps Its Systems
You do not need to switch EHR or practice management software to work with Luxen.
Your Data Stays Protected
Luxen healthcare engagements use HIPAA-compliant workflows, and we execute a business associate agreement before accessing protected health information.
Your Team Knows Who Owns the Work
We use a dedicated team model so responsibility does not disappear into a generic support queue.
You Can Start With Aged AR
Many practices begin with their old AR before moving into the daily revenue cycle. That gives both sides the opportunity to demonstrate results before expanding the engagement.
Vermont Medical Billing FAQs
Why outsource medical billing in Vermont?
Because the deadlines that decide Vermont revenue do not wait for a front desk. The 180-day Medicaid window closes on claims nobody had time to work, and holidays, closures and a pending authorization do not extend it. On the other side, 12 percent interest goes unbilled, recoupment letters go untested against the 12-month limit, and authorization deadlines that would have deemed a request granted pass unrecorded. Outsourcing puts a team on all of it that does not resign.
Do you work with Vermont Medicaid?
Yes. Vermont Medicaid is administered directly by the Department of Vermont Health Access under the Global Commitment to Health waiver, so there are no competing Medicaid managed care plans to enroll with. What matters is the clocks: 180 days from date of service when Medicaid is primary, 365 days when another insurer is primary, 180 days from Medicare’s processing date on crossovers, and 180 days from an adjustment date to resubmit. We work all of them.
How do you handle denied claims?
We work each denial to resolution, document every payer contact, and trace repeated denials back to their source, whether that is eligibility, coding, authorization, filing or routing. Vermont adds two hard limits worth using. Under 18 V.S.A. § 9418 a plan cannot recover a payment made more than 12 months earlier, and it owes you 30 days written notice naming the patient, the date of service, the amount and a specific explanation before it takes anything back.
Is this cost-effective for a small Vermont practice?
Luxen generally charges 3% to 6% of collections. For a small Vermont practice the fee should be measured against money nobody is currently touching: claims that aged past 180 days, interest at 12 percent that was never billed, recoupments taken without testing the 12-month limit or the notice, and authorizations that were deemed granted by statute and never claimed. We look at your AR aging before we quote.
Book a Billing Review
You do not need another sales presentation.
Bring your AR aging, your denial data, and the questions you already have about your billing operation.
In a 30-minute Billing Review, we will look at where your revenue is sitting, where claims are breaking down, what we would prioritize first, and what outsourcing would cost based on your practice.
Send us your AR aging. We will tell you what we believe is recoverable.
